


OSAHS
Vol. 46: Issue 4 - August 2026
Italian Quebec Sleep Questionnaire for assessing quality of life in obstructive sleep apnoea
Authors
Federico Leone
 , Federica Vultaggio
, Fabrizio Salamanca
, Alessandro Bianchi
, Filippo Omenetti
, Andrea Preti
, Carlo Robotti
, Yuliya Germini Moysey
, Francesco Mozzanica
Summary
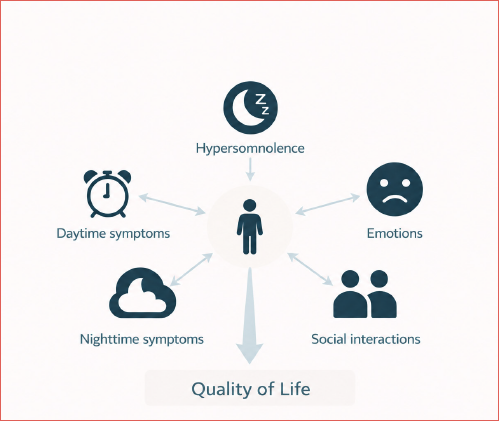
Cover Image
Objective. To develop and validate the Italian version of the Quebec Sleep Questionnaire (I-QSQ) for assessing quality of life (QoL) in patients with obstructive sleep apnoea (OSA).
Methods. The questionnaire was translated, culturally adapted, and back-translated. Internal consistency and test-retest reliability were evaluated in patients with moderate OSA. Normative values were obtained in healthy subjects. Construct and criterion validity were assessed by comparing scores of patients and controls, and by correlating I-QSQ with the Epworth Sleepiness Scale. Responsiveness was examined in patients undergoing sleep surgery.
Results. One hundred-six patients and 173 control subjects completed the I-QSQ without assistance. Internal consistency was acceptable to excellent across domains (Cronbach’s α = 0.71-0.9), and test-retest reliability was high (ICC = 0.88-0.96). Patients scored significantly lower than controls in all domains (p < 0.001). A negative correlation was observed between I-QSQ and Epworth Sleepiness Scale scores (r = –0.54). Post-surgical patients showed significant improvement in I-QSQ total score.
Conclusions. I-QSQ is a reliable, valid, and responsive tool for evaluating QoL in Italian-speaking patients with sleep apnoea and can be effectively used in clinical practice and research.
Introduction
Obstructive sleep apnoea-hypopnoea syndrome (OSAHS) is a chronic disorder characterised by recurrent episodes of partial or complete upper airway obstruction during sleep, resulting in intermittent hypoxaemia and sleep fragmentation 1. OSAHS severity is classified as mild, moderate, or severe based on the frequency of apnoeic and hypopnoeic events per hour of sleep, quantified by the apnoea-hypopnoea index (AHI).
This condition is highly prevalent yet frequently underdiagnosed 2. Kamble et al. 3 reported that mild OSAHS – defined as 5-15 obstructive events per hour of sleep – affects approximately 10-25% of the global adult population. Typical clinical manifestations include habitual or intermittent snoring, recurrent nocturnal awakenings, and witnessed apnoeas.
Beyond its impact on sleep quality, OSAHS is an established independent risk factor for several adverse cardiovascular outcomes, including systemic hypertension, ischaemic heart disease, cardiac arrhythmias, and ischaemic stroke 4. Additionally, the disorder is associated with excessive daytime sleepiness, fatigue, irritability, mood and personality changes, increased risk of motor vehicle accidents, reduced occupational productivity, depression, anxiety, and an overall deterioration in health-related quality of life (HRQoL) 5.
Given the significant impact of OSAHS on individual health and overall well-being, the evaluation of HRQoL in affected patients has gained increasing importance in both clinical practice and research. Even though generic instruments have been employed to assess HRQoL in individuals with sleep disorders 5, they often lack sensitivity to OSAHS-specific clinical features and functional impairments. To address this limitation, OSAHS-specific HRQoL questionnaires have been developed to measure the unique impact of the disorder. Among these, the Sleep Apnea Quality of Life Index (SAQLI) 6 is one of the most widely recognised and validated instruments 7. This test consists of 84 questions divided into 5 domains and is designed to be interviewer-administered. Despite the SAQLI has been translated in several languages (including Chinese, French, Lithuanian, Spanish and Portuguese) and has shown good validity and reliability, its administration remains complex and time-consuming in routine clinical settings 8.
To overcome these limits, Lacasse et al. 9 developed the Quebec Sleep Questionnaire (QSQ). This is a self-assessment questionnaire consisting of 32 questions, grouped into 5 domains: (1) hypersomnolence; (2) daytime symptoms; (3) nighttime symptoms; (4) emotions; and (5) social interactions. Each domain includes 4-7 items, rated on a 7-point scale with lower scores indicating a worse OSAHS-related HRQoL. Compared to the SAQLI, the QSQ is shorter, standardised, self-administered, and demonstrated high validity, reliability, and responsiveness 9. Despite its relevance for clinical assessment, no validated Italian version of the QSQ has been available to date.
The objective of this study was to validate the Italian version of the QSQ (I-QSQ) and to employ it for assessment of OSAHS-specific HRQoL in an Italian cohort. Specifically, the study aimed to: (1) culturally adapt the QSQ into Italian; (2) evaluate the internal consistency and reliability of the questionnaire; (3) establish normative data for the Italian population; and (4) assess its validity and responsiveness.
The underlying hypotheses were that: (1) the I-QSQ can be successfully adapted to the Italian cultural and linguistic context; (2) the Italian version will demonstrate strong internal consistency and reliability; and (3) its validity and responsiveness will be comparable to those of the original version.
This study is of relevance because a validated I-QSQ would represent a valuable tool in clinical practice, particularly in the evaluation of patients OSAHS. It would enhance the understanding of OSAHS-specific HRQoL and support both diagnostic assessment and clinical decision-making regarding therapeutic options.
Materials and methods
The study was divided into several phases: back-translation and cultural adaptation of the QSQ into Italian (Phase 1); internal consistency and reliability analysis (Phase 2); normative data generation (Phase 3); validity analysis (Phase 4); responsiveness analysis (Phase 5) (Tab. I). For Phases 1 and 2, the COSMIN checklist (standards for the selection of health measurement instrument) based on consensus was followed 10.
Participants
Three groups of patients were recruited: control subjects (Group 1) with no history or symptoms of OSAHS; patients with a recent diagnosis of moderate OSAHS but who had not undergone any type of treatment (Group 2); patients with moderate OSAHS who underwent sleep surgery (Group 3). For patients in Groups 2 and 3, moderate OSAHS was diagnosed through home polysomnography (HPsg), defined as an AHI ≥ 15 and < 30, with an apnoea defined as a cessation of oronasal airflow for at least 10 seconds and hypopnoea defined as a ≥ 50% reduction in nasal pressure signal associated with a desaturation > 3% and/or arousal8. Inclusion criteria were age over 18 years and native Italian language proficiency. Additional inclusion criteria for patients in Group 3 were palatal surgery performed by the same surgeon following a proper indication obtained through drug-induced sleep endoscopy (DISE) (performed before the palatal surgery), and AHI< 5 on HPsg performed 6 months after surgery. Exclusion criteria included a history of neoplastic, airway, neurological, rheumatological, haematological, cardiological or endocrinological disorder, and BMI > 30 kg/m2.
All enrolled subjects underwent a specific anamnestic classification for OSAHS patients and an objective nasal and laryngeal evaluation that included a complete examination of the head and neck and a flexible fibreoptic laryngoscopy, performed by means of a fibrescope with flexible optics of 4 mm in diameter, designed to evaluate the morphology of the epiglottis and the volume of the base of the tongue. Daytime symptoms were assessed using the Epworth Sleepiness Scale (ESS) 11, a reliable and validated psychophysical tool used to quantify the probability of falling asleep in different situations of daily life.
All participants managed to complete the I-QSQ autonomously twice. Patients in Group 2 completed an initial I-QSQ at time 0 and a second I-QSQ after 2 weeks to avoid recall of previous responses 12. The third group completed the second I-QSQ 6 months after the scheduled surgery.
Phase 1: back translation and intercultural adaptation of the QSQ into Italian
A process of cross-cultural adaptation of translation and back-translation was carried out. The items of the original QSQ were first translated into Italian by 2 bilingual otolaryngologists experienced in the management of sleep disorders (Step 1: forward translation). Discussion of the translated text with 2 other otolaryngologists with extensive experience in obstructive sleep disorders ensured unanimous agreement and interpretation of the translated version (Step 2: synthesis).
Twenty patients, 10 males and 10 females, with a median age of 55.7 years (range, 27-73), with OSAHS were enrolled in a pilot study (Step 3: pilot study). Each patient independently completed the first translation of the QSQ and discussed the wording and meaning of each questionnaire item with the senior clinician. The wording of the questionnaire was modified to consider the suggestions provided by patients (Step 4: expert group). This new and final version of the I-QSQ (Fig. 1) was then retranslated into English by a qualified professional translator (Step 5: backward translation). This reverse translation has been compared with the original text by the professional translator; no inconsistent translation elements were noted since each element was semantically identical to the original English text. The professionals involved in the intercultural adaptation also discussed the original version, the final translation into Italian and the reverse translation. Finally, the readability of the QSQ was verified by a specialised agency confirming that the text was comprehensible to individuals with a reading level equivalent to 5 years of primary education.
Phase 2: internal consistency and reliability analysis
The aim of this phase was to evaluate the reproducibility of I-QSQ. This was assessed using 2 methods: internal consistency and test-retest reliability. The former assesses the extent to which each element of a factor measures the same underlying construct, while the latter is obtained by administering the same test twice at 2 different time points to a group of individuals. Data from Group 2 participants were used for both analyses. For test-retest reliability analysis the I-QSQ was distributed and compiled twice with an interval of 2 weeks. A variation of 2 days before or after the required 2 weeks was accepted in case of patient needs. A 2-week interval was chosen because no substantial change was expected within this period. Subjects were not granted access to the answers provided to the first questionnaire when filling out the second I-QSQ.
Phase 3: normative data
The purpose of this phase was to establish the baseline distribution for I-QSQ scores in a representative sample of Italian subjects with no history or symptoms of OSAHS. A total of 173 control subjects were enrolled. Participants were stratified into 3 age categories: 18-40 years, 41-60 years, and > 61 years.
Phase 4: validity
The aim of this phase of the study was to assess the degree to which the I-QSQ measures the construct it purports to measure (validity) 11. The validity of the construct was evaluated by comparing the I-QSQ scores obtained in patients with OSAHS (Group 2) and in control subjects (Group 1). Criterion validity was assessed by examining the correlation between I-QSQ scores and ESS results, reflecting the questionnaire’s ability to capture OSAHS-related impairment in HRQoL.
Phase 5: responsiveness
To assess the ability of the I-QSQ to detect important changes over time in the construct to be measured, the I-QSQ scores obtained in patients in Group 3 before and after 6 months from sleep surgery were compared. All the individuals included in this group resolved the OSAHS after surgery as previously described in the inclusion criteria for Group 3.
Statistical analysis
Statistical tests were performed using SPSS 27 statistical software (SPSS, Inc., Chicago, IL). Kolmogorov-Smirnov test was used to test the normality of the distribution of I-QSQ scores among patients and control subjects. Since this test demonstrated that the distribution of the scores was normal in both groups, parametric tests were used 13. The internal consistency of the I-QSQ was evaluated using the Cronbach alpha coefficient. Values between 0.7 and 0.9 have been taken to indicate an acceptable internal consistency 14. Test-retest reliability was assessed by comparing baseline and retesting responses using the internal consistency coefficient (ICC). The correlation strength was considered strong for values above 0.5, moderate for values between 0.3 and 0.5, and weak for values below 0.3 15. ANOVA test was used to evaluate differences in the distribution of I-QSQ scores among the 3 different age groups of control subjects. Student’s t-test was used to compare the results obtained in patients with OSAHS and in the control group. The correlation between I-QSQ and ESS scores was assessed using Pearson test. The distribution of I-QSQ scores obtained in the pre- and post-treatment evaluations were compared using the Student’s t-test. A significance level of α = 0.05 and a statistical power of 0.80 were applied to all analyses.
Results
All patients and control subjects included in the study managed to complete the I-QSQ without needing assistance. The time required to fill out the questionnaire never exceeded 6 minutes. Group 1 was composed of 173 control subjects with a mean age of 49.2 years. Group 2 was composed of 106 patients with a diagnosis of moderate OSAHS and a mean age of 54.7 years. Finally, a total of 33 patients with moderate OSAHS who underwent a successful sleep surgery (postoperative AHI < 5) composed Group 3. Their mean age was 53.1 years.
Phase 2: internal consistency and reliability analysis
Internal consistency was satisfactory with a Cronbach alpha score of a = 0.79, 0.9, 0.8, 0.74, and 0.71 for the Hypersomnolence, Daytime symptoms, Nighttime symptoms, Emotions, and Social interactions subscales respectively. Similarly, the test-retest reliability was also satisfactory for the total score and for all the 5 subscale scores of the questionnaire ranging from an ICC of 0.88 (0.81-0.92) for the Daytime symptom subscale, and 0.96 (0.94-0.98) for the I-QSQ total score.
Phase 3: normative data
The mean age of control subjects (n = 173) was 49.2 years (range, 21-80). Fifty-five percent of subjects were females. Mean I-QSQ scores corresponding to different age categories are reported in Table II. The ANOVA test did not demonstrate a significant difference in the score distribution across the age categories for I-QSQ total score and I-QSQ Nighttime symptoms, Emotions, and Social interactions subscale scores. Conversely, significant differences were observed for the Hypersomnolence and Daytime symptoms subscale scores (p = 0.001 and p=0.019, respectively) were found. In particular, subjects aged between 18 and 40 years scored significantly lower than subjects aged between 41 and 60 years, and > 61 years (p = 0.008 and p = 0.001 at Tukey post hoc test) in the I-QSQ Hypersomnolence subscale and significantly lower than subjects > 61 years (p = 0.019 at Tukey post hoc test) in the I-QSQ Daytime symptoms subscale.
Phase 4: validity
For clinical validity analysis, the I-QSQ scores obtained in patients with OSAHS were compared through Student’s t test to the scores obtained by control subjects. The results (Tab. III) showed that patients with OSAHS scored significantly lower than control subjects on the I-QSQ. The correlation between I-QSQ total score and ESS scores obtained in the group of patients with OSAHS was analysed for concurrent validity. A negative significant correlation was found between these 2 variables (r = -0.540, p = 0.001, Fig. 2).
Phase 5: responsiveness
I-QSQ scores obtained before and after sleep surgery in the 33 patients with OSAHS who experienced a significant improvement of the disease after surgical treatment were compared for responsiveness analysis. The mean I-QSQ total score in the pre-treatment condition was 151.4 ± 44.7, while the post-treatment score was 176.8 ± 21.6. This difference was found significant at Student’s t test (p = 0.013) suggesting a positive evolution of OSAHS-specific HRQoL.
Discussion
In this study the psychometric properties of the I-QSQ were investigated. This questionnaire was developed as a fast, fully self-administered instrument capable of assessing the domains most affected by OSAHS, including hypersomnolence, daytime and nighttime symptoms, emotional impact, and social interactions (Cover figure). Its demonstrated validity, reliability, and responsiveness make it particularly suitable for both clinical settings and research 9. However, a validated Italian version has not been available until now, restricting its applicability in Italian-speaking populations and limiting cross-cultural comparability of HRQoL data 8.
The findings of this study confirm that the I-QSQ is a reliable and valid instrument for assessing OSAHS-related quality of life in Italian-speaking patients. First, the questionnaire demonstrated excellent feasibility: all participants – both asymptomatic individuals and patients with OSAHS – completed the I-QSQ autonomously, and the completion time never exceeded 6 minutes. This is consistent with the intended clinical practicality of the original QSQ and highlights its suitability for routine use, even in settings requiring self-administration or remote data collection 8.
Regarding internal consistency, the Cronbach’s α coefficients of the 5 domains ranged from 0.71 to 0.9, indicating acceptable to excellent homogeneity across items. These values are closely aligned with those reported in the original validation study by Lacasse et al. 9 and with the results of Catalan et al. 16, confirming that the Italian translation preserves the questionnaire’s internal coherence. Similarly, test-retest reliability indices were high across all domains (ICC 0.88-0.96), demonstrating strong temporal stability over time. These results are in line with those reported by Lacasse et al. 9 (ICC 0.82-0.91), and match the quality criteria for measurement properties of health status questionnaires proposed by Terwee et al. 14, thus further supporting the utility of I-QSQ for clinical monitoring of patients with OSAHS 17.
Normative data derived from 173 asymptomatic Italian adults revealed overall stability across age groups for most domains. Significant differences emerged only in the Hypersomnolence and Daytime symptoms domains, with younger participants (18-40 years) reporting worse scores than older groups. This is coherent with age-related variations in daytime alertness and perceived sleepiness described in existing epidemiological and experimental studies, which show that younger adults often exhibit higher daytime sleep propensity and incident excessive daytime sleepiness than older individuals 18-20. The availability of age-stratified normative values strengthens the clinical interpretability of the I-QSQ, offering a reference framework for distinguishing pathological scores from age-related variability.
Construct validity was strongly supported by the comparison between OSAHS patients and healthy controls. As expected, patients exhibited significantly lower scores across all 5 I-QSQ domains and on the total score (all p < 0.001), confirming that the questionnaire is sensitive to disease-related impairment. Concurrent validity was reinforced by the significant negative correlation between the I-QSQ total score and ESS scores (r = -0.540), indicating that worse OSAHS-specific HRQoL is associated with greater subjective sleepiness. This finding is in accordance with the results of Lacasse et al. 9 who reported an inverse significant correlation of r = -0.64 between ESS and QSQ scores.
Finally, responsiveness analysis showed that patients who experienced an objective improvement in OSAHS severity (demonstrated at HPsg) after sleep surgery exhibited a significant increase in I-QSQ total score (from 151.4 ± 44.7 to 176.8 ± 21.6). This result suggests that the I-QSQ can detect meaningful changes over time and is suitable for monitoring postoperative recovery or treatment efficacy. However, effect sizes were not calculated, and a minimal clinically important difference for the I-QSQ has not yet been established. Consequently, although statistically significant changes were observed, the clinical magnitude of improvement cannot be precisely quantified. Future longitudinal studies should aim to define clinically meaningful thresholds for score changes. The magnitude and direction of change were comparable to those reported in studies evaluating HRQoL outcomes following CPAP or surgical interventions in OSAHS populations 21. In particular, Brunetto et al. 21 analysed the QSQ scores obtained in a group of 20 patients with transverse maxillary deficiency and OSAHS (mean AHI, 28.75) before and after 6 months from the application of a mini-implant assisted rapid palatal expansion (MARPE) and demonstrated a significant improvement of QSQ and AHI scores after the treatment. Similar results were reported by Martinez-Garcia et al. 22. In their randomised, multicentre clinical trial on the effect of CPAP treatment in elderly patients with severe OSAHS, the authors reported a significant improvement of the QSQ scores after treatment.
Collectively, these results indicate that the I-QSQ retains the psychometric strengths of the original questionnaire while ensuring cultural and linguistic appropriateness for Italian patients. Its brevity, ease of administration, and strong measurement properties make it an excellent tool for both clinical practice and research, supporting comprehensive assessment of patient-reported outcomes in OSAHS.
From a psychometric perspective, the factorial structure of the Italian version was not formally tested using exploratory or confirmatory factor analysis. The study assumed the original 5-domain structure of the QSQ, in line with several previous cross-cultural validation studies. Nevertheless, future research could benefit from confirmatory factor analysis or modern psychometric approaches such as Rasch modeling to further examine dimensionality.
Study limitations
This study has some limitations that should be acknowledged, while they do not undermine the validity of the findings. First, the responsiveness analysis was performed exclusively in patients undergoing sleep surgery who achieved complete resolution of OSAHS (postoperative AHI < 5). Although this provides clear evidence of sensitivity to change, it represents an optimal and highly selected clinical scenario. Responsiveness of the I-QSQ has not yet been tested following other common therapeutic approaches such as CPAP therapy, mandibular advancement devices, or weight-loss interventions, which should be addressed in future longitudinal studies. An additional limitation concerns disease severity. Only patients with moderate OSAHS were included in the validation phases. While this choice improved sample homogeneity and strengthened internal validity, it may limit generalisability to patients with mild or severe OSAHS, in whom symptom perception and quality-of-life impairment may differ. Further validation studies across the full spectrum of disease severity are therefore warranted. Moreover, patients included in the responsiveness phase were selected through DISE, operated on by the same surgeon, and all experienced surgical success. While this ensured procedural consistency, it may reduce external validity, as real-world surgical outcomes are typically more heterogeneous. Additionally, the exclusion of individuals with obesity (BMI > 30 kg/m2) and relevant comorbidities (cardiovascular, neurological, or endocrine disorders) simplified interpretation of psychometric properties but does not fully reflect the typical clinical OSAHS population. The performance of the I-QSQ in more complex and multimorbid patients remains to be investigated. Finally, although the sample size for psychometric testing was adequate, multicentre studies with broader demographic diversity may provide even stronger evidence for population-wide norms. These considerations offer useful directions for future investigations aimed at expanding the clinical applicability of the I-QSQ.
Conclusions
This study provides the first validated Italian version of the QSQ, confirming that it is a reliable, valid, and responsive instrument for assessing OSAHS-related quality of life in Italian-speaking patients. The I-QSQ showed strong internal consistency across its domains, excellent test–retest reliability, and a marked ability to discriminate between asymptomatic individuals and patients with moderate OSAHS. The generation of age-stratified normative data further enhances the clinical interpretability of the instrument. Additionally, the questionnaire demonstrated sensitivity to postoperative changes, supporting its use for monitoring treatment outcomes over time.
Conflict of interest statement
The authors declare no conflict of interest.
Funding
This research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
Author contributions
All authors contributed to manuscript preparation and approved the final version.
Ethical consideration
The study was approved by the Ethics Committee Comitato Etico Indipendente IRCCS Multimedica (Protocol number: 4150-ID). All procedures of this study were conducted in accordance with the requirements of the World Medical Association’s Declaration of Helsinki. Written informed consent was obtained from each participant/patient for study participation and data publication.
History
Received: December 5, 2025
Accepted: February 9, 2026
Figures and tables
Figure 1. Italian version of QSQ.
Figure 2. Correlation between the Italian version of the Quebec Sleep Questionnaire (I-QSQ) total score and the Epworth Sleepiness Scale (ESS) score.
| Phase of the study | Type of study | Sample clinical characteristics | Age | Sex | |||
|---|---|---|---|---|---|---|---|
| M | F | ||||||
| 1 | Item generation | Item generation | Patients with OSAHS (n = 20) | 55.7 | 10 | 10 | |
| (42-78) | |||||||
| 2 | Internal consistency | Internal consistency | Patients with OSAHS (n = 106) | 54.7 | 73 | 33 | |
| (24-77) | |||||||
| Reliability analysis | Test-retest reliability | Patients with OSAHS (n = 106) | 54.7 | 73 | 33 | ||
| (24-77) | |||||||
| 3 | Normative data | Normative data | Control subjects (n = 173) | 49.2 | 77 | 96 | |
| (21-80) | |||||||
| 4 | Validity | Construct validity | Control subjects (n = 173) | 49.2 | 77 | 96 | |
| (21-80) | |||||||
| Patients with OSAHS (n = 106) | 54.7 | 73 | 33 | ||||
| (24-77) | |||||||
| Criterion validity | Patients with OSAHS (n = 106) | 54.7 | 73 | 33 | |||
| (24-77) | |||||||
| 5 | Responsiveness | Comparison pre- and post-therapy | Patients with OSAHS (n = 33) | 53.1 | 19 | 14 | |
| (25-75) | |||||||
| OSAHS: obstructive sleep apnoea syndrome. | |||||||
| 18-40 | 41-60 | > 61 | P | |
|---|---|---|---|---|
| (n = 68) | (n = 58) | (n = 47) | ||
| Hypersomnolence | 32.9 ± 6.1 | 35.9 ± 6.2 | 36.7 ± 3.9 | 0.001 |
| (31-34) | (34-37) | (35-37) | ||
| Daytime symptoms | 51.9 ± 11.4 | 55.5 ± 9.6 | 57.3 ± 8.8 | 0.019 |
| (49-55) | (53-58) | (54-59) | ||
| Nighttime symptoms | 40.9 ± 7.3 | 41.1 ± 5.9 | 40.6 ± 5.5 | 0.316 |
| (39-43) | (39-42) | (38-42) | ||
| Emotional | 27.2 ± 4.7 | 27.9 ± 5.1 | 27.7 ± 4.7 | 0.287 |
| (26-28) | (26-29) | (26-29) | ||
| Social interactions | 22.5 ± 3.9 | 23.5 ± 3.5 | 23.7 ± 2.4 | 0.642 |
| (21-23) | (22-24) | (23-24) | ||
| I-QSQ total | 175.4 ± 28.6 | 183.9 ± 24.3 | 186.1 ± 19.9 | 0.176 |
| (168-182) | (177-190) | (180-191) |
| Control subjects | Patients with | P | |
|---|---|---|---|
| (n = 173) | OSAHS (n = 106) | ||
| Hypersomnolence | 34.9 ± 5.8 | 30.7 ± 10.3 | < 0.001 |
| (31-37) | (9-38) | ||
| Daytime symptoms | 54.6 ± 10.3 | 45.4 ± 16.3 | < 0.001 |
| (49-59) | (21-61) | ||
| Nighttime symptoms | 40.9 ± 6.4 | 30.3 ± 10.9 | < 0.001 |
| (39-43) | (11-48) | ||
| Emotional | 27.6 ± 4.8 | 24.1 ± 8.1 | < 0.001 |
| (26-29) | (12-34) | ||
| Social interactions | 23.2 ± 3.4 | 18.3 ± 6.5 | < 0.001 |
| (21-24) | (10-27) | ||
| I-QSQ total | 181.2 ± 25.4 | 148.2 ± 47.9 | < 0.001 |
| (168-191) | (73-211) |
References
- Sleep-related breathing disorders in adults: recommendations for syndrome definition and measurement techniques in clinical research. Sleep. 1999;22:667-689.
- Rundo J. Obstructive sleep apnea basics. Cleve Clin J Med. 2019;86:2-9. doi:https://doi.org/10.3949/ccjm.86.s1.02
- Kamble P, Theorell-Haglöw J, Wiklund U. Sleep apnea in men is associated with altered lipid metabolism, glucose tolerance, insulin sensitivity, and body fat percentage. Endocrine. 2020;70:48-57. doi:https://doi.org/10.1007/s12020-020-02322-0
- Peppard P. Increased prevalence of sleep-disordered breathing in adults. Am J Epidemiol. 2013;177:1006-1014. doi:https://doi.org/10.1093/aje/kws342
- Saddki N, Mohamad H, Mohd Yusof N. Validity and reliability of the Malay version of Sleep Apnea Quality of Life Index. Health Qual Life Outcomes. 2013;11. doi:https://doi.org/10.1186/1477-7525-11-100
- Flemons W, Reimer M. Development of a disease-specific health-related quality of life questionnaire for sleep apnea. Am J Respir Crit Care Med. 1998;158:494-503. doi:https://doi.org/10.1164/ajrccm.158.2.9710070
- Stucki A, Cieza A, Schuurmans M. Content comparison of health-related quality of life instruments for obstructive sleep apnea. Sleep Med. 2008;9:199-206. doi:https://doi.org/10.1016/j.sleep.2007.04.005
- Abma I, van der Wees P, Veer V. Measurement properties of patient-reported outcome measures in adults with obstructive sleep apnea. Sleep Med Rev. 2016;28:18-31. doi:https://doi.org/10.1016/j.smrv.2015.07.006
- Lacasse Y, Bureau M, Sériès F. A new standardised and self-administered quality of life questionnaire specific to obstructive sleep apnoea. Thorax. 2004;59:494-499. doi:https://doi.org/10.1136/thx.2003.009605
- Mokkink L, Terwee C, Patrick D. The COSMIN study reached international consensus on taxonomy and definitions of measurement properties. J Clin Epidemiol. 2010;63:737-745. doi:https://doi.org/10.1016/j.jclinepi.2010.02.006
- Johns M. A new method for measuring daytime sleepiness: the Epworth Sleepiness Scale. Sleep. 1991;14:540-545. doi:https://doi.org/10.1093/sleep/14.6.540
- Cardella A, Riva G, Preti A. Italian version of the Brief Questionnaire of Olfactory Disorders (Brief-IT-QOD). Acta Otorhinolaryngol Ital. 2023;43:252-261. doi:https://doi.org/10.14639/0392-100X-N2212
- Vittinghoff E, Glidden D, Shiboski S. Regression Methods in Biostatistics. Springer; 2012. doi:https://doi.org/10.1007/978-1-4614-1353-0
- Fawcett T. An introduction to ROC analysis. Pattern Recognit Lett. 2006;27:861-874. doi:https://doi.org/10.1016/j.patrec.2005.10.010
- Terwee C, Bot S, de Boer M. Quality criteria for measurement properties of health status questionnaires. J Clin Epidemiol. 2007;60:34-42. doi:https://doi.org/10.1016/j.jclinepi.2006.03.012
- Catalán P, Martínez A, Herrejón A. Internal consistency and validity of the Spanish version of the Quebec Sleep Questionnaire. Arch Bronconeumol. 2012;48:107-113. doi:https://doi.org/10.1016/j.arbres.2011.10.011
- Prieto L, Lamarca R, Casado A. Assessment of the intraclass correlation coefficient in clinical findings. Med Clin (Barc). 1998;110:142-145.
- Jaussent I, Morin C, Ivers H. Incidence and risk factors of daytime sleepiness in a 5-year longitudinal study. Sci Rep. 2017;7. doi:https://doi.org/10.1038/s41598-017-01547-0
- Honda M. Are old people sleepier than young people?. Sleep Biol Rhythms. 2024;22:299-300. doi:https://doi.org/10.1007/s41105-024-00532-1
- Dijk D, Groeger J, Stanley N. Age-related reduction in daytime sleep propensity and slow-wave sleep. Sleep. 2010;33:211-223. doi:https://doi.org/10.1093/sleep/33.2.211
- Brunetto D, Moschik C, Dominguez-Mompell R. Mini-implant assisted rapid palatal expansion effects on adult OSA. Prog Orthod. 2022;23. doi:https://doi.org/10.1186/s40510-021-00397-x
- Martínez-García M, Chiner E, Hernández L. Obstructive sleep apnoea in the elderly: role of CPAP. Eur Respir J. 2015;46:142-151. doi:https://doi.org/10.1183/09031936.00064214
Downloads
License

This work is licensed under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.
Copyright
Copyright (c) 2026 Società Italiana di Otorinolaringoiatria e chirurgia cervico facciale
How to Cite
- Abstract viewed - 134 times
- PDF downloaded - 65 times